doi.org/10.20986/resed.2026.1320
REVIEW
Gender differences in pain behavior: do sex hormones influence nociceptive outcome? Narrative review
Diferencias en el comportamiento del dolor: ¿las hormonas sexuales influyen en el resultado nociceptivo? Revisión narrativa
Juan Camayo Zorrilla1 https://orcid.org/0000-0002-0226-9762
Juan David Peláez Martínez2 https://orcid.org/0000-0003-0032-6417
Valentina Morales Arias2 https://orcid.org/0009-0003-7032-8503
Manuela Rodríguez Giraldo2 https://orcid.org/0009-0006-7587-0694
David Alejandro Ríos Pineda2 https://orcid.org/0000-0002-4933-8606
Rafael Ordoñez Lizarralde1 https://orcid.org/0000-0003-0618-1714
Fredy Ariza1 https://orcid.org/0000-0001-5012-5125
1Anesthesiology Department. Fundación Valle del Lili. Cali, Colombia.
2Universidad ICESI. Cali, Colombia
ABSTRACT
Introduction: Pain is a complex phenomenon shaped by biological, psychological, and social factors. Among these, sex differences are increasingly recognized due to the higher prevalence of chronic pain in women and their greater sensitivity to nociceptive stimuli. Sex hormones have been proposed as key, though not exclusive, contributors to these differences. This review aimed to explore the evidence on the factors that determine sex differences in pain perception.
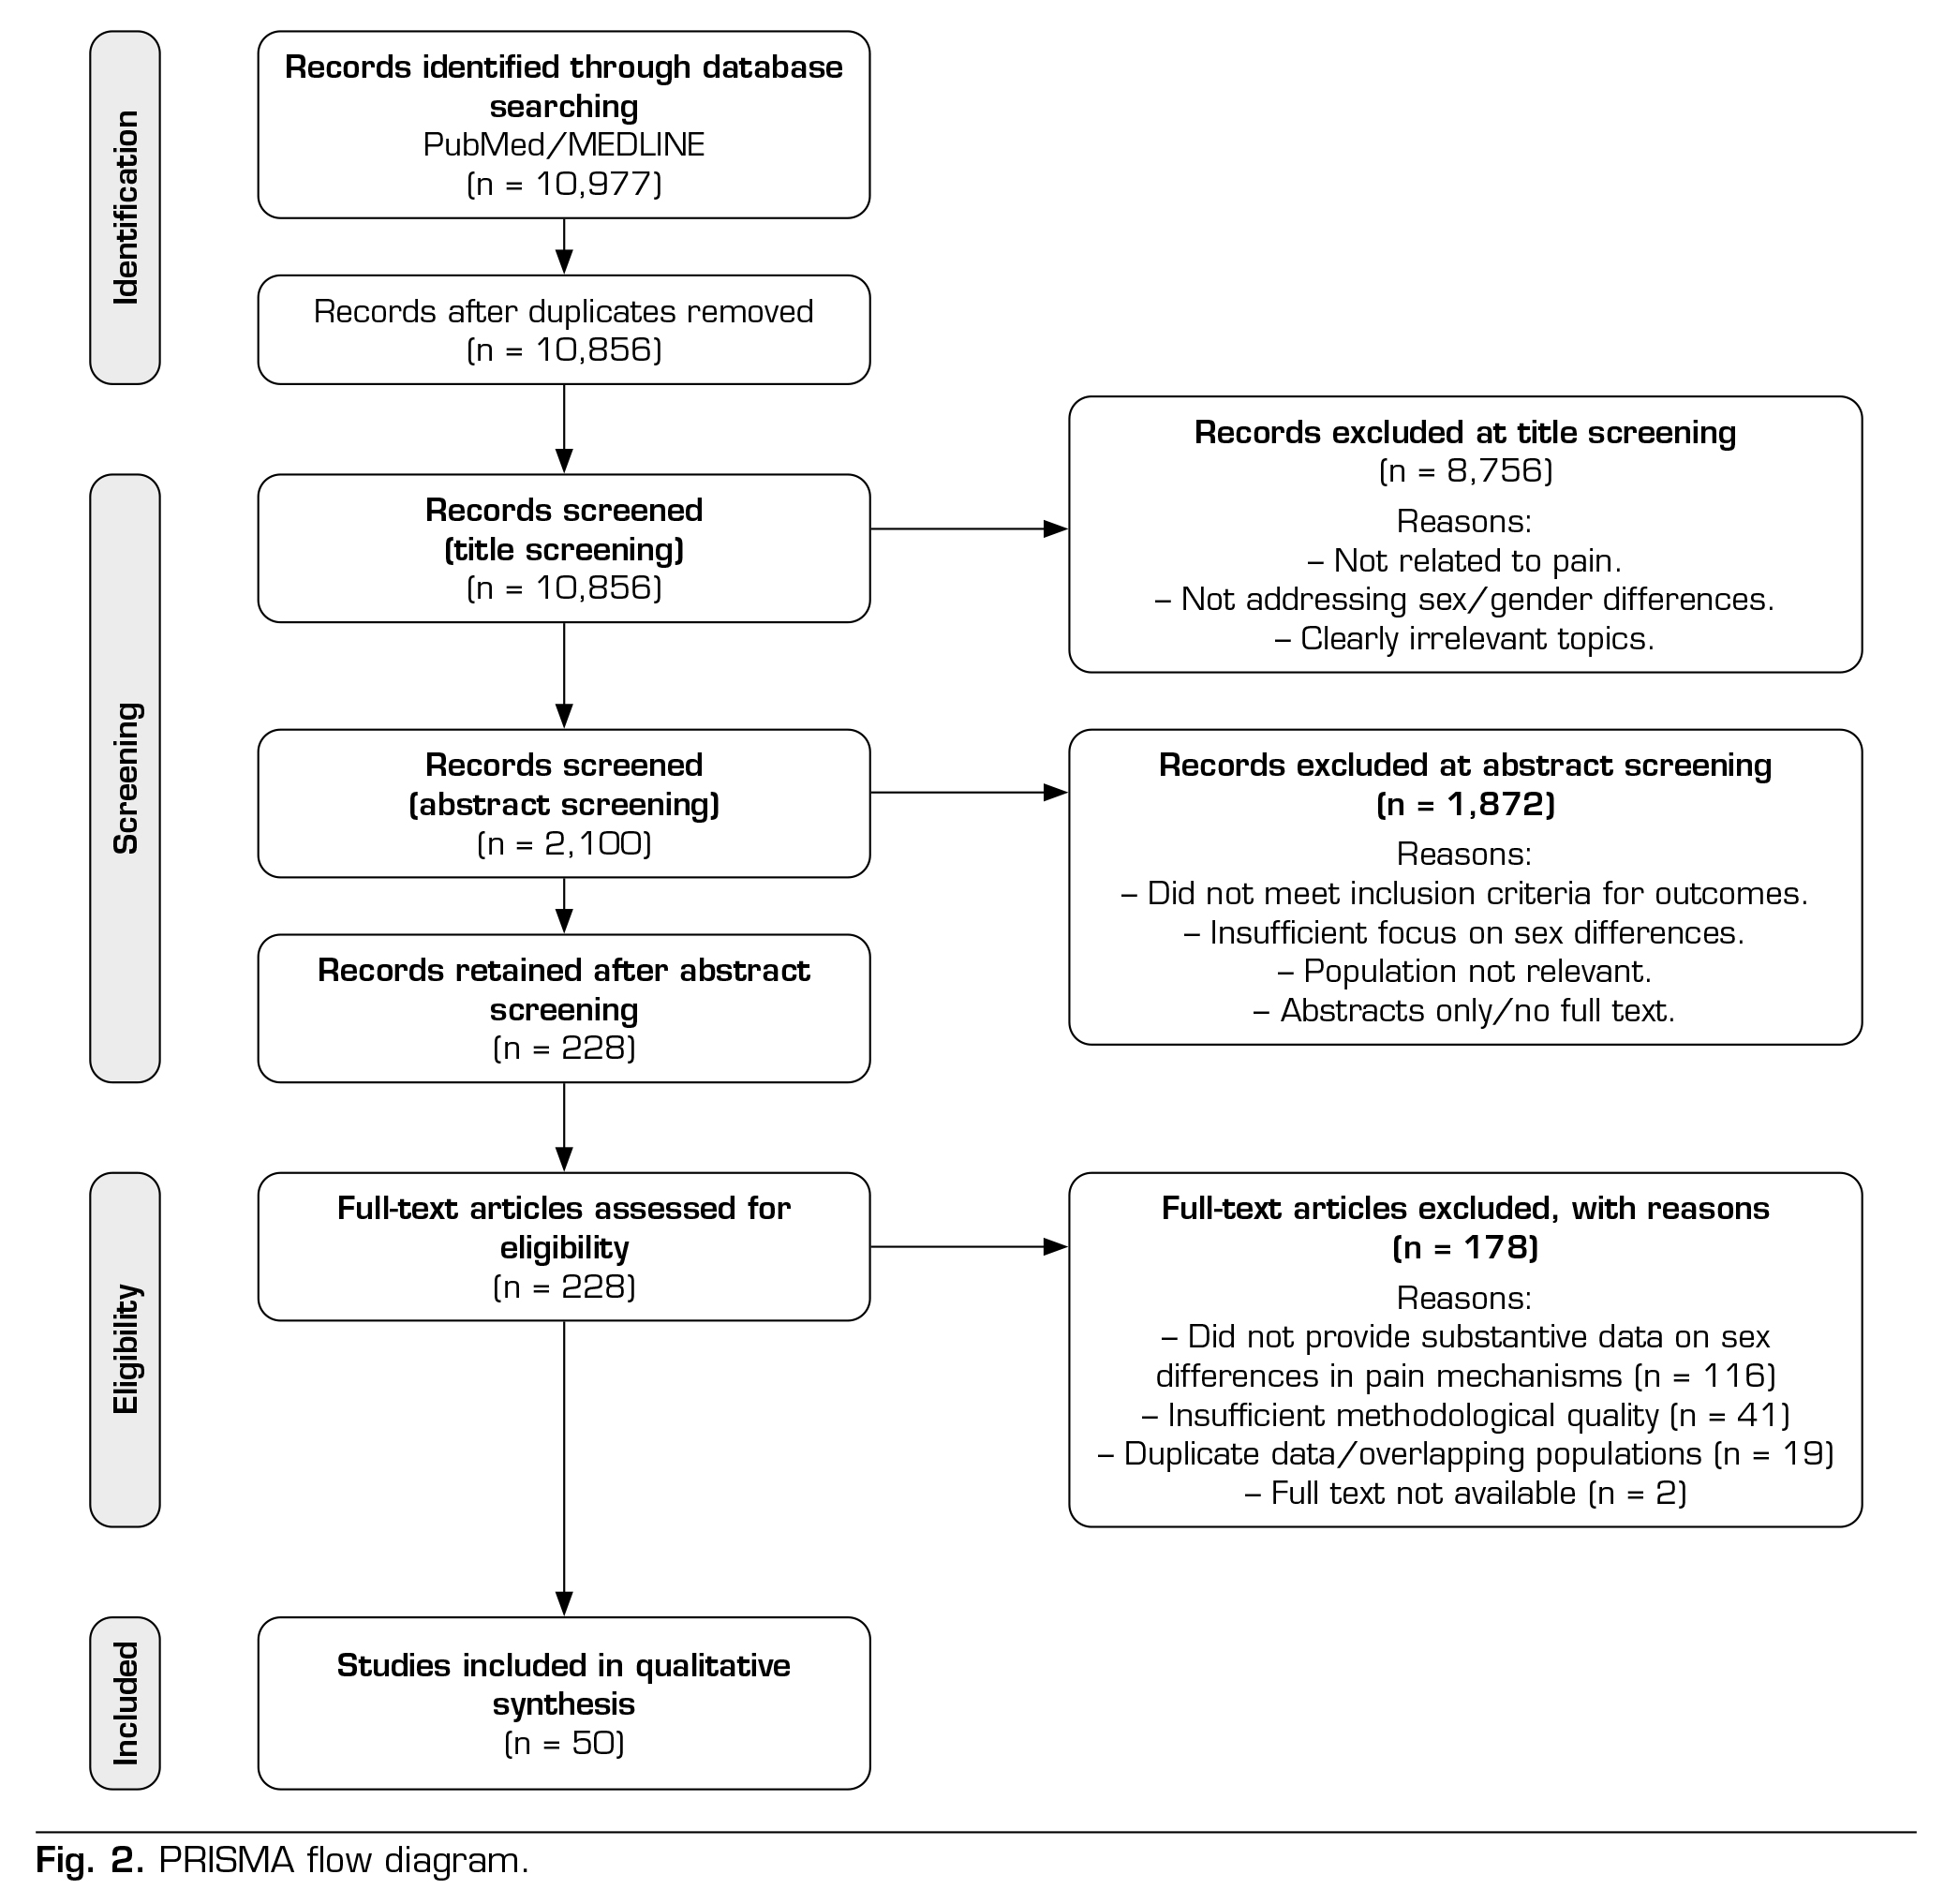
Methods: A review was conducted using PubMed/MEDLINE (January 1, 2024). From 10,977 initial records, title screening by five independent reviewers reduced the pool to 2,100 records. Abstract screening yielded 228 articles for full text review. Extracted data included study design, population characteristics, pain outcomes, hormonal variables, and key findings. Following assessment, 50 articles met eligibility criteria and were included.
Results: Women experience more experimental pain and show higher prevalence of chronic pain conditions such as migraine, temporomandibular disorder, and osteoarthritis. Hormonal influences, including the dual effects of estrogen and progesterone and the potentially protective role of testosterone, appear to be context-dependent and insufficient to fully explain these differences. Neurobiological mechanisms, as well as differences in opioid system responses, contribute to sex-specific pain perception. Clinically, women exhibit greater sensitivity to opioids but also a higher incidence of adverse effects. Psychosocial factors further modulate pain experience through bidirectional interactions with biological mechanisms.
Conclusions: Sex hormones appear to account only partially for sex differences in pain perception, as their effects depend on interactions with neurobiological and psychosocial mechanisms. Understanding these determinants may contribute to a more comprehensive, sex-informed approach to pain assessment and management. Future research should prioritise standardised reporting of sex and gender variables, rigorous assessment of hormonal status, and longitudinal designs capturing hormonal transitions, in line with current international recommendations.
Key words: Analgesia, female, male, pain, sex hormones
RESUMEN
Introducción: El dolor es un fenómeno complejo determinado por factores biológicos, psicológicos y sociales. Entre ellos, las diferencias de sexo han cobrado relevancia por la mayor prevalencia de dolor crónico en mujeres y su mayor sensibilidad a estímulos nociceptivos. Las hormonas sexuales han sido señaladas como un factor clave, aunque no exclusivo, en estas diferencias. Esta revisión tuvo como objetivo explorar la evidencia sobre los factores que determinan las diferencias de sexo en la percepción del dolor.
Métodos: Se realizó una revisión narrativa de la literatura, utilizando PubMed/MEDLINE (1 de enero de 2024). De un total de 10.977 registros iniciales, el cribado de títulos realizado por cinco revisores independientes redujo el grupo a 2100 registros. El cribado de resúmenes resultó en 228 artículos para revisión de texto completo. Los datos extraídos incluyeron el diseño del estudio, las características de la población, los resultados relacionados con el dolor, las variables hormonales y los hallazgos clave. Tras la evaluación, 50 artículos cumplieron con los criterios de elegibilidad y fueron incluidos.
Resultados: Las mujeres presentan mayor frecuencia de dolor experimental y de condiciones dolorosas crónicas como migraña, trastorno temporomandibular y osteoartritis. Las influencias hormonales, incluyendo los efectos duales de los estrógenos y la progesterona, y el papel potencialmente protector de la testosterona, parecen ser dependientes del contexto e insuficientes para explicar completamente estas diferencias. Los mecanismos neurobiológicos, así como las diferencias en la respuesta del sistema opioide, contribuyen a la percepción del dolor específica por sexo. En el ámbito clínico, las mujeres presentan mayor sensibilidad a los opioides, pero también una mayor incidencia de efectos adversos. Los factores psicosociales modulan además la experiencia dolorosa a través de interacciones bidireccionales con mecanismos biológicos.
Conclusiones: Las hormonas sexuales parecen explicar solo parcialmente las diferencias de sexo en la percepción del dolor, ya que su efecto depende de la interacción con mecanismos neurobiológicos y psicosociales. El entendimiento de estos determinantes puede contribuir a un abordaje más integral y sensible al sexo en la evaluación y el manejo del dolor. La investigación futura debería priorizar el reporte estandarizado de variables de sexo y género, la evaluación rigurosa del estado hormonal y el uso de diseños longitudinales que capten las transiciones hormonales, en consonancia con las recomendaciones internacionales actuales.
Palabras clave: Analgesia, femenino, masculino, dolor, hormonas sexuales.
Correspondencia
Fredy Ariza Cadena
fredy.ariza@fvl.org.co
Recibido: 19-08-2025
Aceptado: 09-09-2026
Camayo Zorrilla J, Peláez Martínez JD, Morales Arias V, Rodríguez Giraldo M, Ríos Pineda DA, Ordoñez Lizarralde R y Ariza F. Gender differences in pain behavior: do sex hormones influence nociceptive outcome? Narrative review. Rev Soc Esp Dolor. 2026: 1320_1-20
INTRODUCTION
Pain is influenced by several factors that precipitates an ambiguous response, as proposed by the International Association for the Study of Pain (IASP) “Pain is an unpleasant sensory and emotional experience associated with, or resembling that associated with, actual or potential tissue damage… is always a personal experience influenced to varying degrees by biological, psychological, and social factors” (1). Sex differences in response to pain have been widely described (2), suggesting that sex-specific pain mechanisms may contribute to the varied effectiveness of treatments in males and females (3,4).
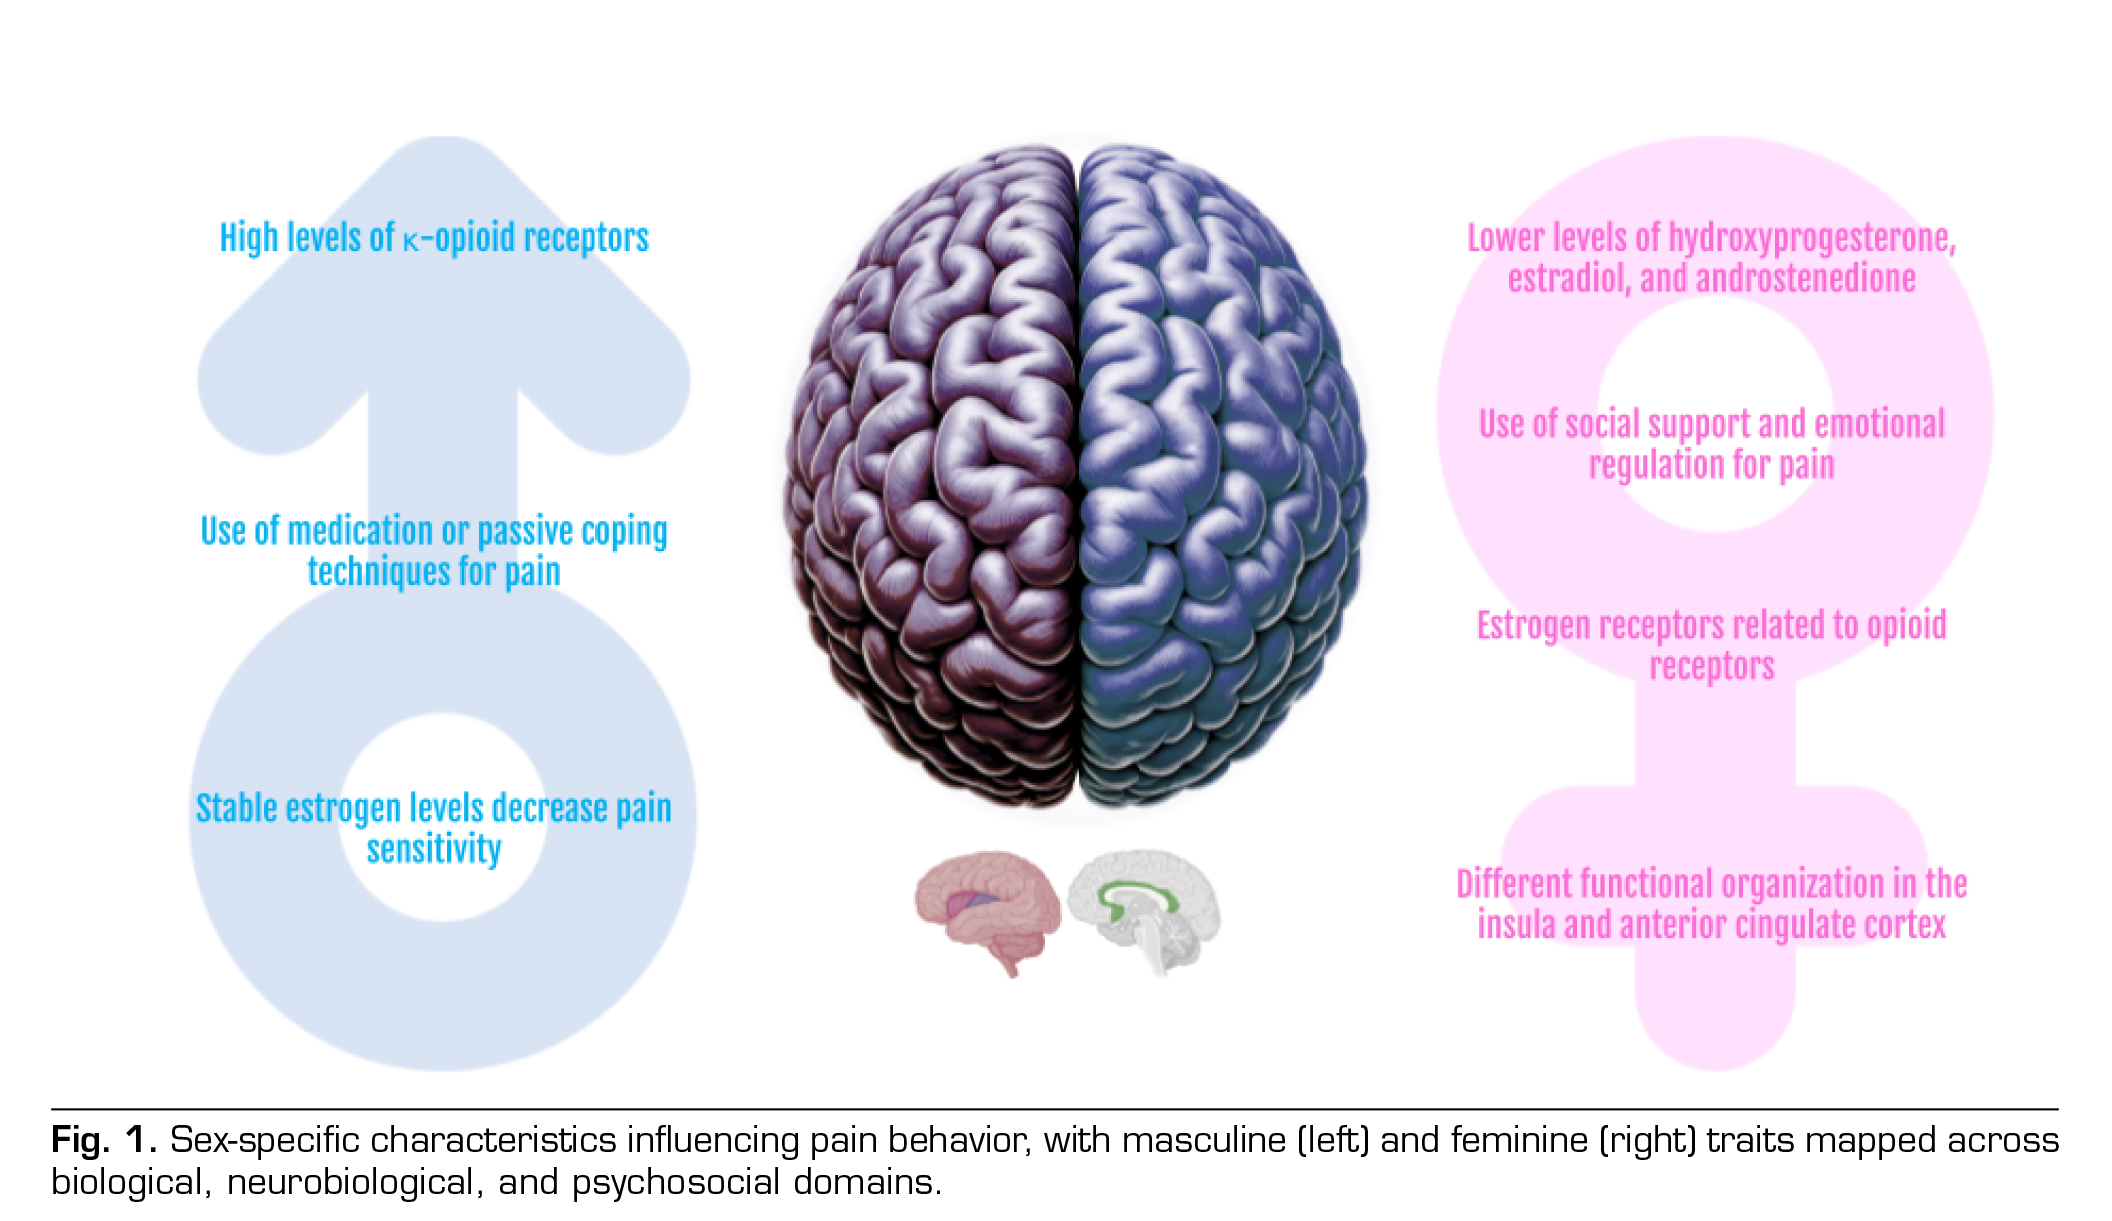
Pain has been shown to differ between sexes, with females exhibiting a more substantial response to experimental and clinical pain with a higher risk of developing chronic inflammatory pain conditions (5,6,7). Given the contradictory results of data on the mechanism underlying these differences, sex hormones emerged as a logical yet controversial topic that accounts for most of the inconsistencies in nociceptive responses (4,8,9). It raises the question of whether the gap in pain response can be attributed solely to sex hormones or if it should be considered within a broader spectrum that includes psychosocial, environmental, and behavioral factors. The key sex specific characteristics influencing pain behavior in males and females are illustrated in Figure 1.
In this review, we evaluate the literature that encompasses sex differences in pain perception and its various factors determining the outcomes of nociception and outcomes related to the role of sex hormones in pain perception between sexes, opioid system responses, neurobiological mechanisms, and psychosocial factors within an integrated biopsychosocial framework.
METHODS
Study design and research question
We constructed our narrative review aiming to answer the investigation question: What is the evidence available on the factors determining the differences in pain perception between men and women, including the specific role of sex hormones, opioid system responses, neurobiological mechanisms, and psychosocial factors within a biopsychosocial framework? Ethical approval was not necessary because of the nature of the investigation.
Search strategy
We conducted a search on the PubMed/Medline database on January 1.st 2024, using natural language terms and MeSH terms: “Pain Threshold”, “Sex Characteristics”, “Gender”, “Hormones” and “Chronic Pain”, including a list of synonyms, and combining them with the Boolean operators “AND” and “OR”, which led to a total of 10,977 results.
Inclusion and exclusion criteria
The inclusion criteria for this review focused on original research articles, including experimental animal studies, human experimental pain studies, clinical observational studies, and randomized controlled trials; as well as systematic reviews, meta-analyses, and narrative reviews addressing sex differences in pain mechanisms. Eligible populations comprised human subjects of all ages and animal models, focusing on outcomes such as pain threshold, tolerance, intensity, chronic pain prevalence, neurobiological mechanisms, opioid system function, analgesic efficacy, and psychosocial factors. Inclusion was limited to published full text articles with no language restrictions. Excluded unpublished studies, stand alone abstracts, and methodological papers lacking specific data on sex differences. Additionally, any studies that did not address sex or gender as a primary variable in pain outcomes were omitted.
Study selection process
During the initial title-screening stage, five independent reviewers (JCZ, JDPM, VMA, MRA, DAR) screened all retrieved records to exclude clearly irrelevant studies, such as those not related to pain or not addressing sex/gender differences, reducing the pool to approximately 2,100 records. In the subsequent abstract-screening stage, abstracts were independently assessed by two reviewer groups (JCZ and JDPM; VMA, MRA, DAR), ensuring that each article was evaluated by at least two reviewers. Discrepancies in study classification (inclusion, exclusion, or uncertain) were resolved through discussion and consensus. This process yielded 228 articles for full-text review. Full texts were subsequently retrieved and independently assessed by the same reviewer groups. Ultimately, 50 articles met all eligibility criteria and were included in the final analysis, providing substantive data on sex differences in pain mechanisms (Figure 2).
Data extraction
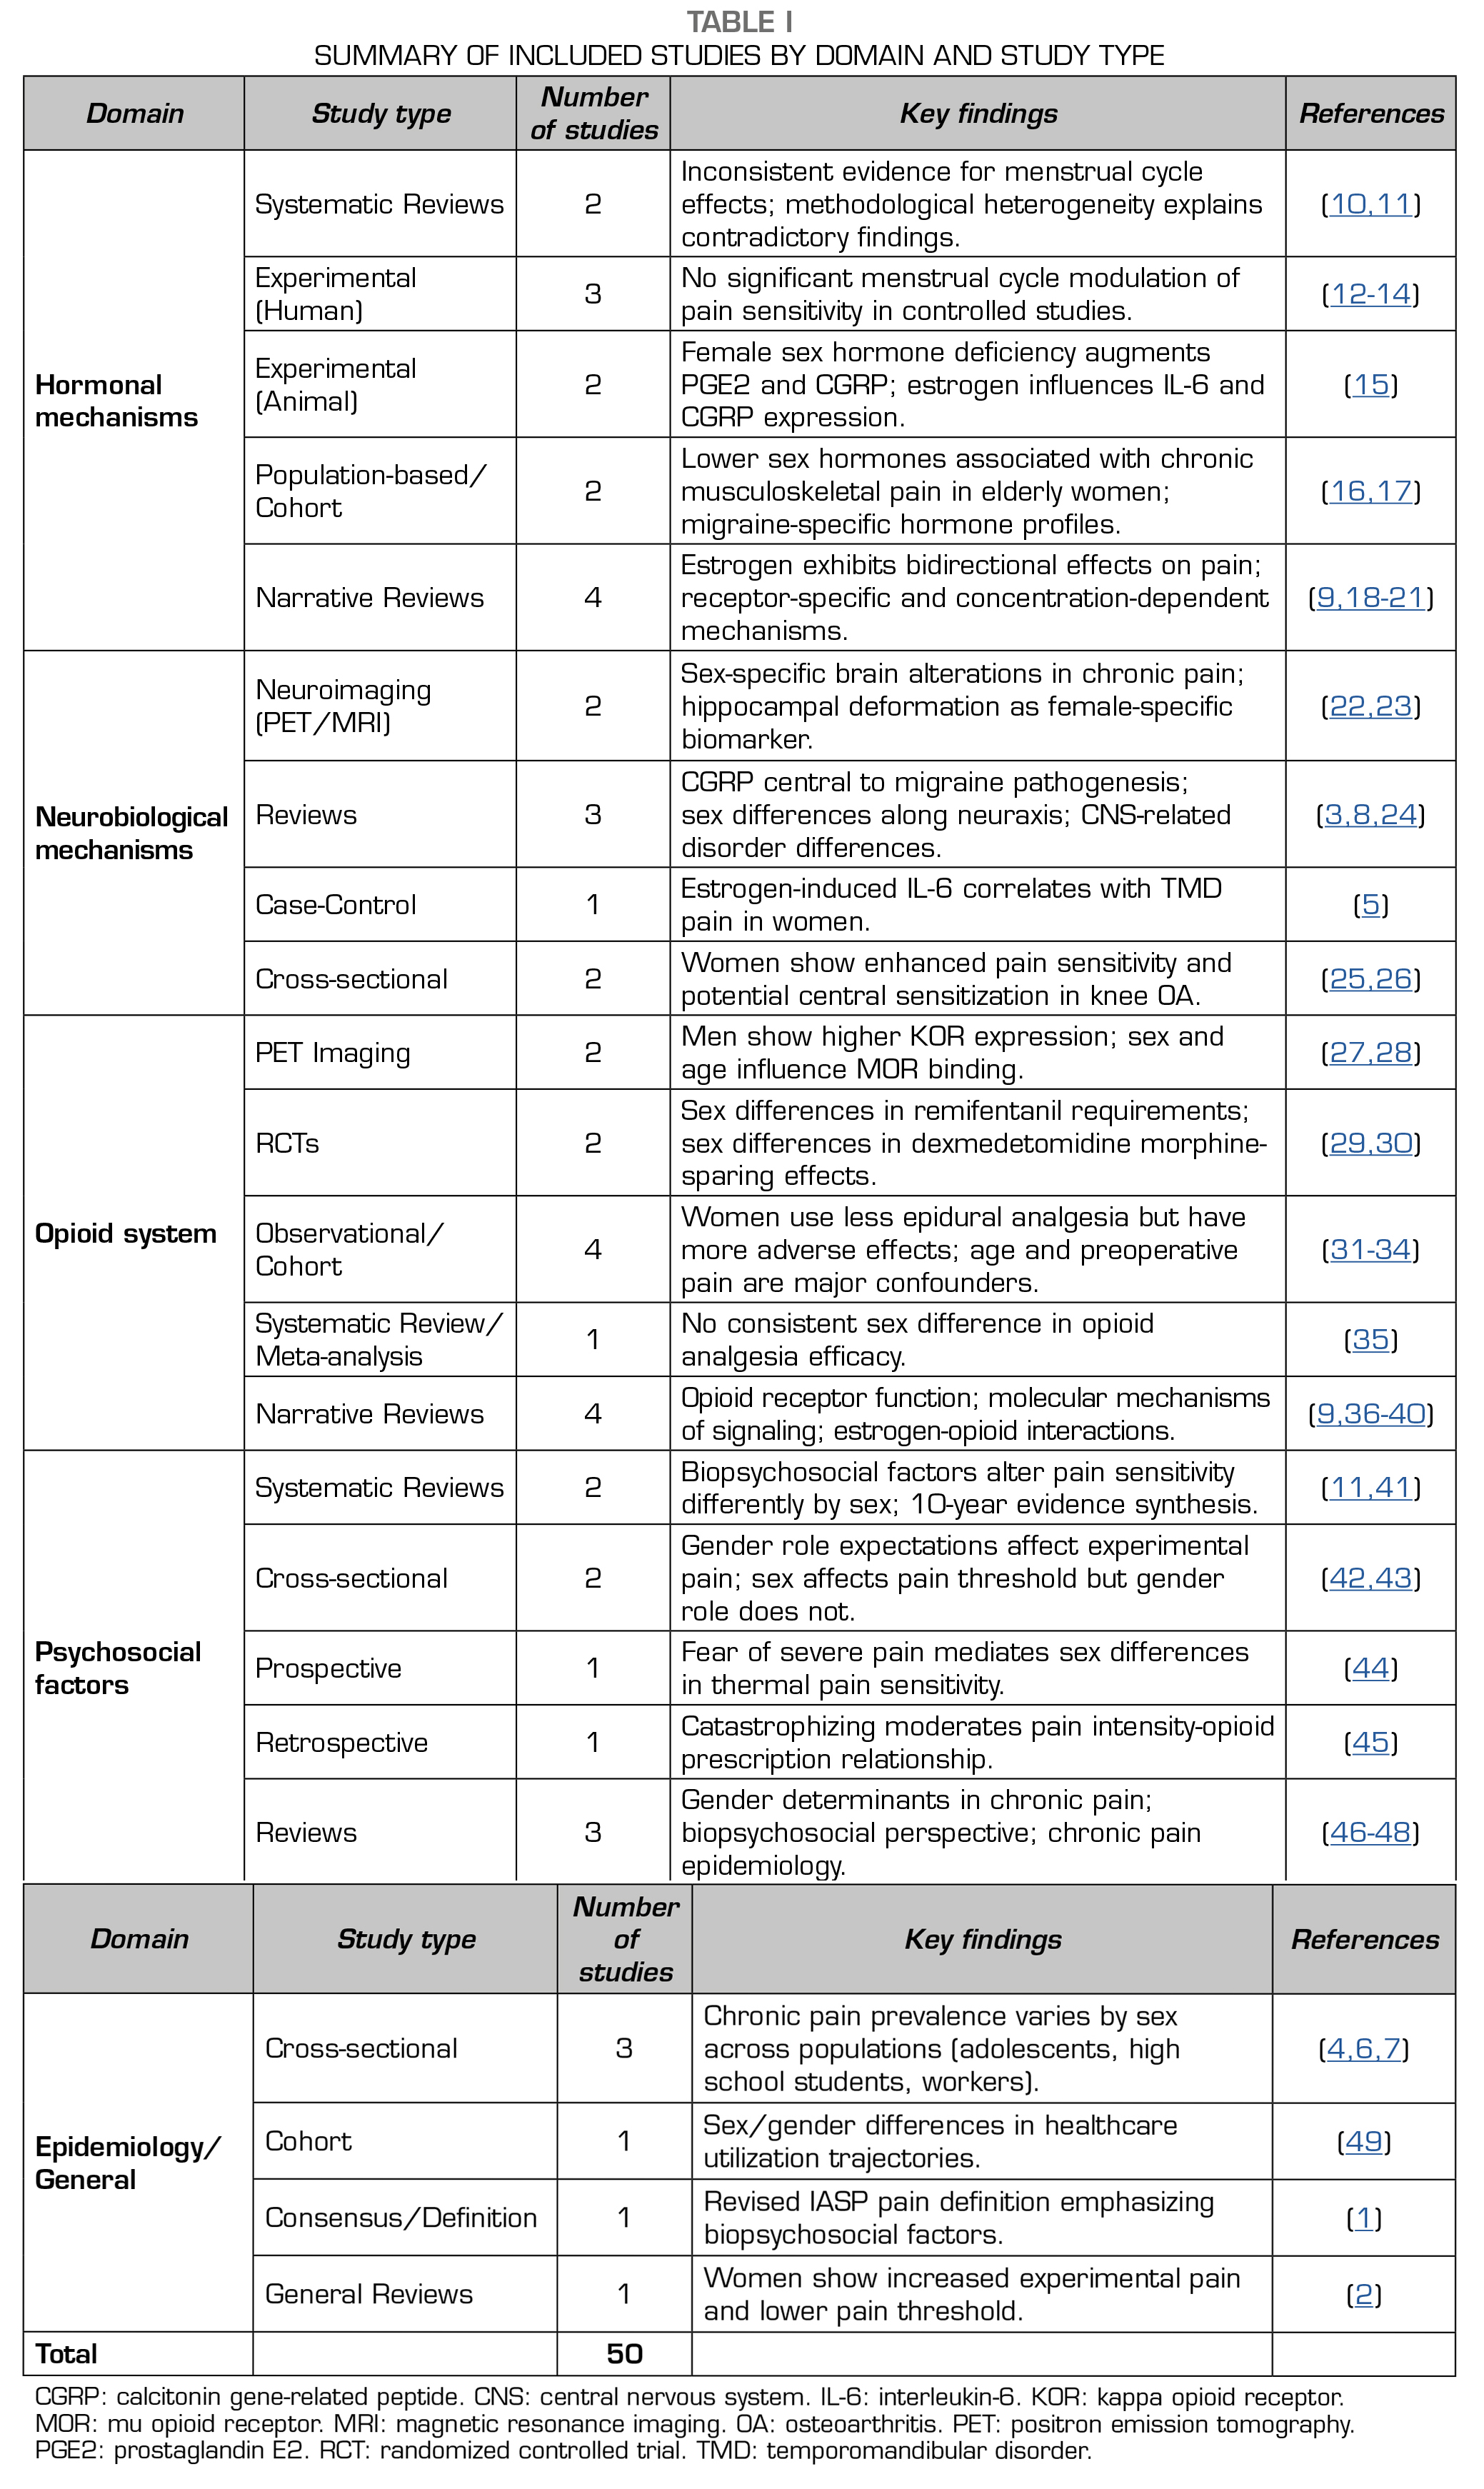
For each included study, the following variables were extracted: study identification (first author, publication year, journal), study design, population characteristics (sample size, age range, sex distribution, health status), pain model/condition, hormonal variables measured, primary outcomes, key findings related to sex differences, and authors conclusions. Data extraction was performed independently by the five reviewers (JCZ, JDPM, VMA, MRA, DAR) with verification by a senior author (FA). The characteristics of included studies are summarized in Table 1, with detailed information for each individual study provided in Supplementary Table S1.
Quality assessment
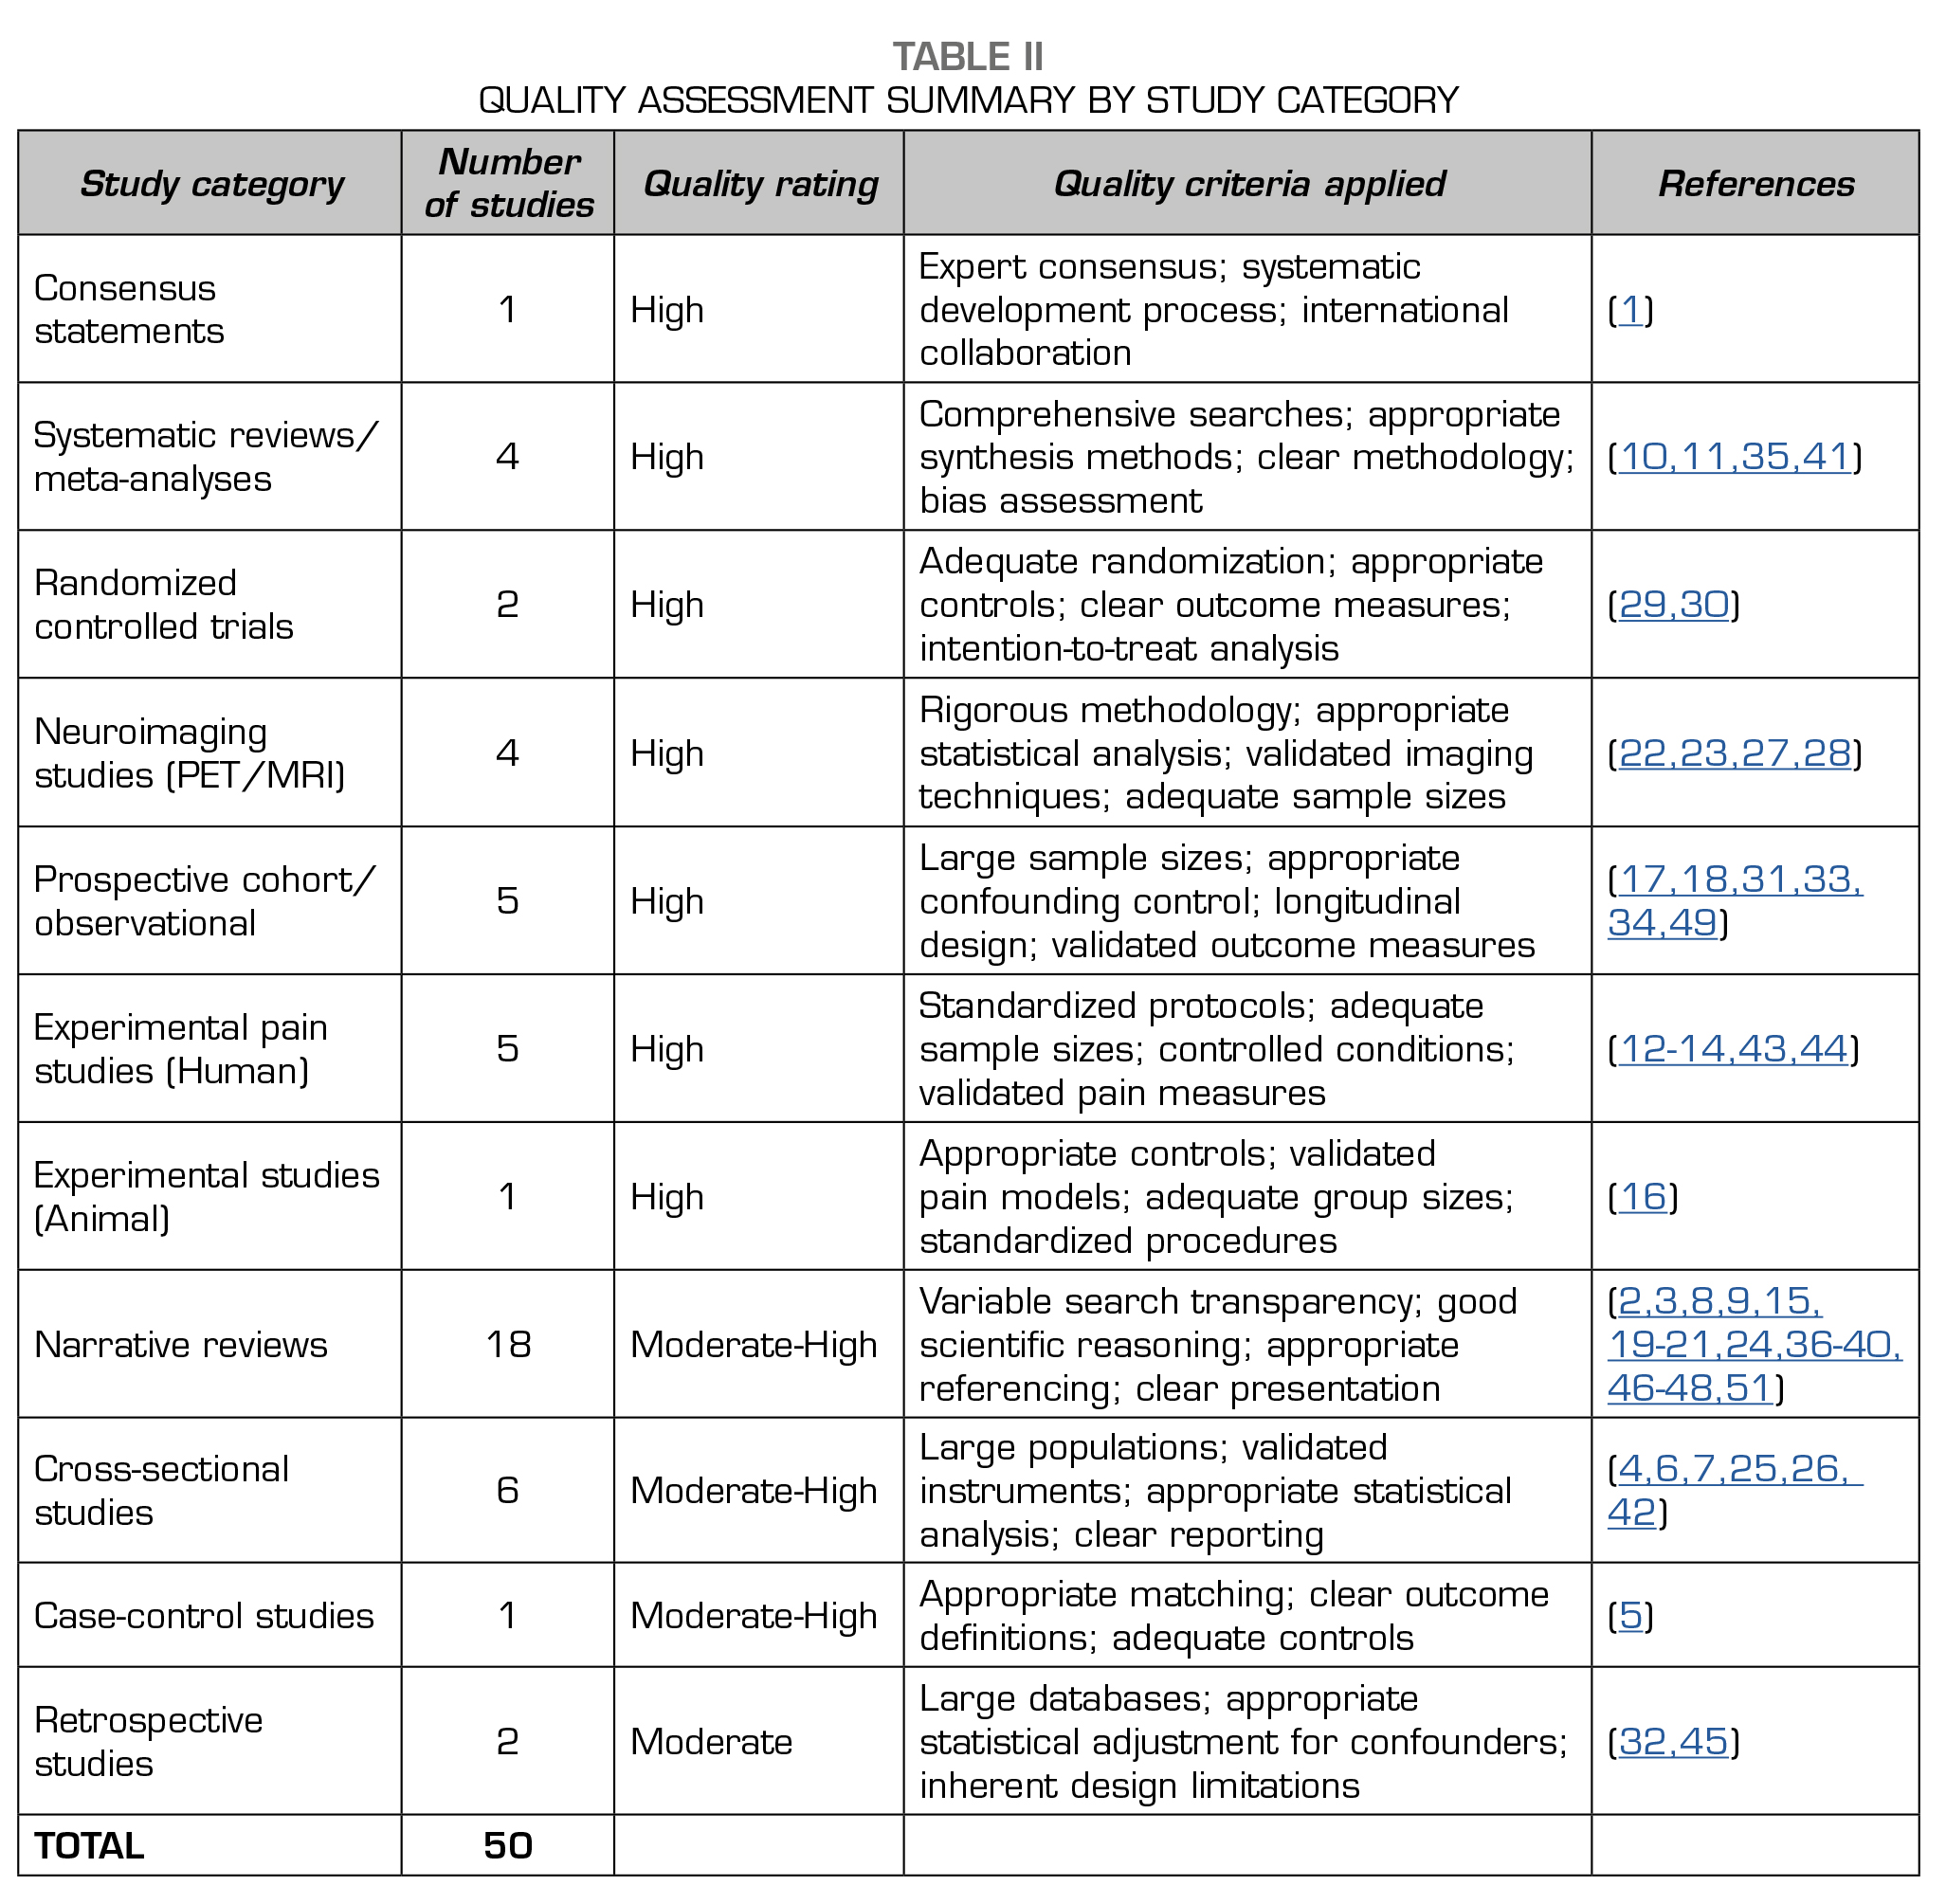
Quality assessment was conducted using the Scale for the Assessment of Narrative Review Articles (SANRA) as a guiding framework (50), adapted for the diverse study types included in this review. For narrative reviews, we evaluated justification of the article’s importance, statement of aims, description of literature search, referencing, scientific reasoning, and appropriate presentation of data. For primary research articles, quality was assessed based on sample size adequacy, control for confounding variables, appropriate statistical methods, and clarity of reporting. For systematic reviews and meta-analyses, we evaluated search comprehensiveness, synthesis methods, and bias assessment. Randomized controlled trials were
assessed for adequate randomization, appropriate controls, and clear outcome measures. Neuroimaging studies were evaluated for rigorous methodology, appropriate statistical analysis, and use of validated techniques. Observational studies were assessed for sample size, confounding control, and longitudinal design where applicable. Two reviewer groups (JCZ and JDPM; MRA and DAR) assessed study quality, with discrepancies resolved through consensus discussion. Studies were categorized as High quality (meeting all or most criteria with minimal methodological concerns), Moderate-High quality (meeting most criteria with minor limitations), or Moderate quality (adequate methodology with notable limitations). The quality assessment results are presented in Table 2.
Data synthesis
Given the focus of this study on identifying the factors determining the outcomes of nociception and the influence of sex hormones on pain perception between sexes, we divided the study into each determining factor: sex hormones and experimental pain, sex differences in chronic inflammatory pain conditions, endogenous opioid receptors and therapeutic analgesia, and psychosocial factors, with emphasis on the bidirectional integration between biological and psychosocial domains.
RESULTS
A total of 50 articles were included in the final qualitative synthesis (Figure 2). The distribution by study type and thematic domain is presented in Table 1. Quality assessment revealed that the majority of included studies were of moderate to high methodological quality (Table 2). Detailed characteristics of individual studies are provided in Supplementary Table S1. As illustrated in Figure 1, the factors influencing pain behavior differ substantially between sexes, encompassing hormonal, neurobiological, opioid system, and psychosocial domains, each of which is examined in detail below.
Sex hormones and experimental pain
Significant differences in pain response and immunomodulatory characteristics between female and male mice have been observed in experimental animal models of acute and chronic pain. Female rats elicit more Interleukin 6 (IL-6) production and greater expression of calcitonin gene-related peptides (CGRP) than males, mainly influenced by estrogens (15). Moreover, experimental models found more significant levels of CGRP in the peripheral and central nervous systems that may contribute to increased nociceptive transmission. Clinically, patients experiencing migraine attacks show increased levels of CGRP, which has been associated with the pathogenesis of this disorder (24). Furthermore, the downregulation of CGRP, along with a decreased expression of serotonin reuptake transporter in trigeminal nerves may regulate pain responses in migraine and temporomandibular disease in women (16,19).
Thus, one of the most evident and logical differences in pain perception between sexes is the exposure to fluctuating hormone levels, supporting the role of sex hormones as an important, yet controversial, factor in pain modulation. Although some studies have identified anti-inflammatory responses in the central and peripheral nervous system attributed to some sex hormones which enhance an anti-nociceptive response by downregulating aromatase receptors, the debate continues (2,5,9,10,15,20,21).
According to the available data, we encountered contradictory results for these explanations. In this review, we discuss two hypotheses.
Hypothesis 1: The increase in pain sensitivity can be attributed to the constant fluctuation of estrogen during the reproductive years of healthy women which affects neural modulation homeostasis (4,8,10,17). This hormonal variation leads to the activation of the endogenous opioid system, which in turn downregulates opioid receptors in the central nervous system (CNS), increasing pain sensitivity and allodynia (51). A population-based study showed that women with chronic pain had lower levels of hydroxyprogesterone, estradiol and androstenedione. These reduced hormone levels increase the risk of developing chronic inflammatory disorders during their childbearing years (18).
Hypothesis 2: Contrary to some findings, other reports suggest a poor relationship between gonadal hormones and the increased outcomes of nociceptive sensitivity among healthy women. Studies have shown that changes in the concentration of estrogen and progesterone do not correlate with phase-related (follicular and luteal phase) algesia in those exposed to experimental pain stimuli, accounting for pain outcomes to other factors (12,13). Balter et al. compared women with chronic neck pain who have normal menstrual cycles and women taking oral contraceptives, finding no significant differences in pain sensitivity among the phases of the menstrual cycle for both groups (12). Interestingly, research also indicates the hypoalgesic influence of testosterone in pain response in healthy women (20). Despite these findings, the results remain inconsistent, highlighting the need for further research.
Sex differences in chronic inflammatory pain conditions
Research consistently shows that women are more likely to experience higher prevalences of inflammatory chronic pain disorders than men (5,7,49). However, the mechanisms underlying these differences are not fully understood. Conversely, male mice demonstrated more robust anti-inflammatory immune response and antibody-mediated reactivity (24). Furthermore, a prospective observational study found that the exogenous use of estrogen can modulate opioid and serotonin regulatory pathways. This modulation increases the perception and intensity of headaches by promoting Nitride-Oxide (NO) release, therefore identifying estrogen as a potential trigger for migraine attacks (14).
Patients experiencing migraine attacks exhibit distinct sex-specific phenotypes in brain function, structure, and pain perception, which can be attributed to neuroanatomical differences between females and males (25). A review by Gupta et al. highlighted variations in neuroimaging and brain responses to pain; notably, women displayed a unique functional organization of the insula and anterior cingulate cortex, impacting cognitive processes involved in modulating chronic pain. Furthermore, women showed morphological changes in the sensory-motor cortex, leading to increased sensory reactivity to pain. These findings suggest that sex differences significantly influence the brain’s functional organization related to pain behavior, with these differences becoming even more pronounced when controlling for sex hormones (22). In chronic pain conditions, deformations of the hippocampus have been detected as a geometric distortion of the shape of the hippocampus in patients with chronic back pain compared to healthy volunteers; this has emerged as a robust diagnostic biomarker. Intriguingly, this biomarker’s relevance appears to be exclusive to women, underscoring a potential sex-specific effect (23).
Women suffering from temporomandibular disorder (TMD) have shown a pro-inflammatory state characterized by increased levels of IL-6, which contributes to the development of synovitis and arthralgia of the temporomandibular joint (5). Furthermore, Bartley et al. compared a substantial cohort of women and men with knee osteoarthritis, alongside experimental pain tasks to elucidate pain responses irrespective of sex hormone levels. The findings revealed that women are more likely to experience greater experimental pain intensity and a lower pain threshold (26).
Although the previously described research highlights significant sex differences between men and women, with sex hormones playing a pivotal role, the studies reviewed also present notable limitations. To address these, future research should employ more standardized criteria for experimental pain stimuli and pain processing tasks. Additionally, larger sample sizes and the inclusion of cohorts with chronic pain conditions —as opposed to solely healthy volunteers— are essential for enhancing the statistical power of these studies (11,41).
Endogenous opioid receptors and nociception
Three major types of endogenous opioid receptors are expressed. µ (MOR), k (KOR), and d (DOR). The Opioid receptor-like orphan (ORL) receptor, which was included later, is not discussed in this review. Beyond their well-known role in analgesia and pain modulation through mediating nociceptive pathways in the brain, these receptors are implicated in numerous physiological functions. They are expressed across the immune system and contribute to the membrane homeostasis and the functioning of the gastrointestinal, respiratory, and cardiovascular systems. The widespread expression might underlie many of the side effects associated with exogenous opioids (36). Additionally, the interaction of these receptors with mood-related behavior and dopaminergic reward pathways might explain the high dependency potential observed with opioids profile (37,38). In experimental clinical settings, sex differences in receptor-ligand binding dynamics have been observed in parts of the CNS during acute pain episodes, influenced by sex hormones (39).
Sex differences in therapeutic analgesia
Research has revealed differences in therapeutic responses between men and women. Specifically, Vijay et al. found that the gray matter of men exhibited a higher expression of KOR than women, demonstrating a greater affinity for KOR antagonists like naltrexone (27). This suggests pronounced sex differences in the modulation of the opioid system, with estrogen receptors playing a crucial role as modulators in the CNS (40). They influence the availability and expression of the opioid receptors, leading to increased sensitivity to therapeutic opioids in women and a higher availability of multiple opioid receptors, especially MOR across multiple brain regions (27,28,40). Additionally, a randomized clinical trial highlighted that women showed greater sensitivity to opioid receptor modulation. Sex differences in the degradation of remifentanil by esterases, which are influenced by sex hormones, contribute to higher effect-site concentrations of synthetic opioids (29).
Schnabel et al. observed reduced usage of patient controlled-epidural analgesia in women undergoing major surgery. This phenomenon may be attributed to a higher concentration of opioid receptors in women’s brains compared to men’s, which leads to a better response to opioids but also higher incidence of adverse effects such as postoperative nausea, vomiting and motor blockade. Consequently, this could result in less frequent administration of medication and an increased risk of insufficient pain relief in the post anesthesia care unit (31). Furthermore, Lo et al. discovered that among various confounding factors, sex is the only significant predictor of side effects, which subsequently reduces opioid consumption in women (32).
A systematic review suggests that despite women’s decreased opioid consumption (35), they often experience reduced incidence of postoperative pain as seen in the Swedish National Cohort Spine Register (SWESPINE), reflecting greater improvement of pain and quality of life 2 years from baseline (33). However, such differences might also be influenced by age and pre-existing chronic pain conditions, which are significant confounders in postoperative pain management, particularly in older women who exhibit greater pain intensity and higher opioid consumption. Nonetheless, the increased sensitivity to postoperative pain in some women does not translate to clinically relevant differences, as both sexes report comparably satisfactory pain relief outcomes (34). Beyond differences in opioid system response, women exhibit varied adrenergic receptor activity that impacts opioid response. Specifically, alpha-2 adrenergic receptors play a crucial role, demonstrating analgesic and sedative effects in pain behavior. Notably, there are sex differences in the opioid-sparing effects of alpha-2 adrenergic agonists, such as Dexmedetomidine (30).
Psychosocial factors influencing pain outcome
Sex and gender roles: recently, sex and gender have become controversial topics in understanding pain behavior. It is essential to distinguish between the two terms. “Sex” refers to the biological development of an individual, including genetic makeup and sexual organs. In contrast, gender encompasses a broader range of factors, including environmental, sociocultural, and psychological contexts, such as gender roles (41). The definition and development of gender roles are shaped by social and behavioral conditionings. Society often imposes norms that lead women to be more likely to feel and report pain, while men are encouraged to display stoicism, resulting in lower pain scores and less willingness to report pain. This dichotomy highlights the gender pain theorem and underscores the importance of considering these broader aspects when evaluating pain behavior (42). However, Kröner-Herwig et al. found that while sex significantly influences pain pressure threshold and tolerance, gender roles do not significantly affect pain responses (43).
The mechanism for these differences remains unclear, and research results are often controversial and contradictory. A population-based study found that a predisposition towards certain gender roles influenced pain perception: masculinity was associated with lower pain intensity, while attraction to feminine romantic partners correlated with higher experimental pain tolerance among homosexual, bisexual, and heterosexual women. Social stress was linked to lower health quality and pain ratings. However, despite these findings, gender differences in pain perception are not entirely understood, and further research is necessary (2).
Pain coping strategies: One of the critical aspects of pain behavior is coping with noxious stimuli. Women reported more adaptive strategies, focused on social support, positive reappraisals and emotional self-regulation, providing a greater sense of control and some habituation to the intensity of the pain (46,47,48). In contrast, men prefer pharmacotherapy or passive coping techniques such as social distraction focused on problem resolution. For this reason, they are better responders and more adherent to physical exercise, physiotherapy or rehabilitation than women (46,47,48). Also, a systematic review found that women who experience pain are more likely to use maladaptive coping strategies, which predispose them to chronic pain and worse functional ability. Therefore, men prefer therapeutic modalities focused on physical exercise or those therapies that include behavioral pain management components. However, they respond better to cognitive-behavioral and emotional self-regulation modalities (47,48).
According to pain coping strategies, catastrophizing plays an essential role in nociception as it can anticipate pain. As seen in a retrospective observational study where catastrophizing increased frequency, intensity, and disability in women, a direct correlation between female sex, opioid consumption, and pain coping strategies enhances (34,45). Interestingly, one prospective study associated sex differences in pain to fear, accounting as one of the factors for the progression from acute to chronic low back pain. When psychosocial and environmental factors are controlled, sex differences in pain perception become less pronounced (44).
DISCUSSION
Sex differences in pain perception are consistently observed across experimental and clinical settings, with women showing greater pain sensitivity and a higher prevalence of several chronic pain conditions (2,5,6,7). In line with the objective of this review, the available evidence indicates that these differences cannot be explained solely by sex hormones, but are better understood through the interaction of hormonal, neurobiological, opioid-related, and psychosocial mechanisms within a biopsychosocial framework (4,8,9).
The contribution of sex hormones to pain modulation remains important, but its interpretation is complicated by methodological heterogeneity across studies. In particular, discrepancies in the menstrual cycle–related findings appear to be largely explained by inconsistent phase classification, inadequate hormonal verification, single time-point measurements, and insufficient sample sizes (10,11). When more rigorous study designs are applied, hormonal fluctuations seem to exert a more limited and context-dependent effect on nociceptive responses, and may not fully account for the observed sex differences (12,13). In addition, estrogen appears to have receptor-specific and concentration-dependent effects, with either pro- or antinociceptive actions depending on the biological context, which may further explain the variability reported across the literature (20).
Beyond hormonal influences, stable neurobiological differences also appear to contribute to sex-specific pain processing. Functional differences in brain regions involved in pain modulation, particularly the insula and anterior cingulate cortex, suggest that women and men may process nociceptive information through partially distinct central mechanisms (22). Structural findings, such as hippocampal shape deformation identified as a potential biomarker of chronic back pain in women, further support the existence of sex-related differences that may persist independently of acute hormonal states (23). Likewise, differential expression of CGRP and related pain modulatory pathways may provide a biologically plausible basis for sex-specific vulnerability in conditions such as migraine and temporomandibular pain (15,16,19,24).
Greater mu-opioid receptor availability in women (28), despite variable clinical responses, highlights the complexity of translating receptor expression into functional outcomes. Women consume less opioid via patient-controlled analgesia yet report comparable pain relief (31,35), suggesting increased sensitivity to opioid effects. A higher incidence of adverse effects in women (31,32) further supports the need for sex-informed analgesic strategies, while age and preoperative pain remain important confounders (34).
Contemporary models emphasise that psychosocial factors are bidirectionally integrated with biological systems (41,47). Empirical evidence supports this interaction: catastrophising has been shown to modulate pain–opioid relationships in a sex-specific manner (45), while fear of severe pain mediates sex differences in thermal pain sensitivity (44). Notably, when psychosocial variables are controlled, observed sex differences in pain responses become less pronounced, and in the context of multicomponent interventions integrating cognitive, emotional, and behavioural strategies, these differences may no longer be evident (46,47).
From a clinical and translational perspective, these findings highlight the need for more tailored approaches to pain assessment and management. Sex-related differences in opioid response, both in terms of analgesic efficacy and adverse effect profiles, should be taken into account when designing analgesic strategies (30,31,34). Recent neuroimmune evidence further refines this interpretation, suggesting that the traditional binary model of sex-specific pain mechanisms is overly simplistic, with multiple immune cell types, including macrophages, T cells, and B cells, contributing to persistent pain in a context-dependent manner (52). In addition, IL-10–producing monocytes have been shown to promote inflammatory pain resolution via signalling to sensory neurons, with faster resolution observed in males in both experimental and human studies, supporting a sex-dependent neuroimmune mechanism (53). Future research should align with international consensus frameworks, such as the 2025 PAINDIFF Network, prioritising standardised reporting of sex variables, rigorous assessment of hormonal status, longitudinal designs capturing hormonal transitions, and integrative models combining neuroimmune, hormonal, and psychological mechanisms (54).
This review is subject to some limitations, including restriction to a single database (PubMed/MEDLINE) and the inherent subjectivity of narrative synthesis. Although the search was conducted in January 2024, selected recent studies were incorporated in the discussion to contextualise the findings. In addition, the predominance of Western populations may limit generalisability.
CONCLUSION
Sex differences in pain perception are unlikely to be explained solely by sex hormones, but rather arise from the interaction of biological, neurobiological, and psychosocial factors. While hormonal influences remain relevant, their effects appear context-dependent and insufficient to fully account for the observed variability. Emerging evidence suggests that neurobiological and neuroimmune processes, together with psychosocial modulation, contribute to these differences. These findings highlight the importance of adopting a more nuanced, sex-informed approach to pain assessment and management. Future research should prioritise standardised reporting of sex and gender variables, rigorous assessment of hormonal status, and longitudinal designs capturing hormonal transitions. In line with the PAINDIFF Network recommendations, integrative approaches combining neuroimmune, hormonal, and psychosocial domains will be essential to improve the validity and clinical translation of sex-informed pain research.
AUTHORS CONTRIBUTIONS
JCZ: Conception of the original project, study planning, reference search and interpretation, writing and final approval of the manuscript.
JDPM: reference search, organization, interpretation and final writing of the manuscript.
VMA: reference search, organization, interpretation and final writing of the manuscript.
MRG: reference search, interpretation and final writing of the manuscript.
DAR: reference search, interpretation and final writing of the manuscript.
ROL: Reference interpretation, writing and final approval of the manuscript.
FA: Reference interpretation, writing and final approval of the manuscript.
ASSISTANCE FOR THE STUDY
None.
FINANCIAL SUPPORT AND SPONSORSHIP
None.
CONFLICT OF INTEREST
None.
PRESENTATIONS
None.
APPRECIATION
None.
REFERENCES